Photo by Towfiqu Barbhuiya / Unsplash
Top 10 GLP-1 Alternatives and Next-Generation Weight Loss Treatments of 2026
GLP-1 medications like Ozempic deliver results—but $1,000+ monthly injections, weekly dosing, and muscle loss concerns leave millions seeking alternatives. In 2026, the landscape has shifted: clinical trials show oral therapies matching injection efficacy, dual-hormone treatments delivering 22% average body weight loss without weekly injections, and breakthrough triple-hormone therapies achieving 24%+ results in real-world studies. This guide reviews all 10 evidence-backed alternatives, comparing FDA approval timelines, peer-reviewed efficacy data, actual 2026 pricing from major pharmacies, and medically-documented side effect profiles—so you can find your match: whether you need to eliminate injections, cut costs, prevent GI side effects, or access the most recent clinical breakthroughs.
Top10Grid lets the community re-rank anything — this order is our editors' pick for now; use the buttons below to vote it up or down.

Current Rankings
- –
Tirzepatide, marketed as Zepbound for weight management and Mounjaro for type 2 diabetes, is a once-weekly subcutaneous injection that simultaneously activates two incretin hormone receptors: GLP-1 (glucagon-like peptide-1) and GIP (glucose-dependent insulinotropic polypeptide). This dual mechanism produces greater reductions in caloric intake, enhanced energy metabolism, and superior glycemic control compared to GLP-1 agonism alone. In the SURMOUNT-1 trial (N=2,539, 72 weeks), patients on the highest 15 mg dose lost an average of 22.5% of their body weight, with 50-57% achieving 20% or more weight loss. The landmark SURMOUNT-5 head-to-head trial (N=751, 72 weeks) showed tirzepatide users lost 20.2% vs 13.7% for semaglutide -- a 47% greater relative reduction. Critically, 19.7% of tirzepatide patients lost 30% or more body weight, versus just 6.9% of semaglutide patients. GI discontinuation was lower with tirzepatide (2.7%) than semaglutide (5.6%). Side effects include nausea, diarrhea, vomiting, constipation, and abdominal pain. Black box warning for thyroid C-cell tumors (based on rodent studies) contraindicates use in patients with personal or family history of medullary thyroid carcinoma or MEN2 syndrome. Cost: List price $1,000-$1,086/month. Lilly self-pay vial program $399-$549/month. Savings card as low as $25/month for commercially insured. Medicare Part D covers Zepbound at $50/month via GLP-1 Bridge Program from July 2026. Eligibility: adults with BMI 30+ or BMI 27+ with a weight-related comorbidity.
- –
Retatrutide is Eli Lilly's investigational triple receptor agonist, simultaneously activating GLP-1, GIP, and glucagon receptors. Glucagon agonism directly elevates metabolic rate and stimulates fat oxidation, complementing appetite suppression and insulin-sensitizing effects of the GLP-1/GIP axis. The Phase 3 TRIUMPH-1 trial (N=2,339, 80 weeks, results announced May 2026) achieved 28.3% average total body weight loss at the 12 mg maximum dose, with 45.3% of participants losing 30% or more body weight. Placebo weight loss was 3.9%. These results approach or match outcomes of Roux-en-Y gastric bypass -- the highest average weight loss ever recorded in a Phase 3 drug study. Dose-dependent results: 17.6% (4 mg), 23.7% (9 mg), 28.3% (12 mg). Discontinuation due to adverse events: 4.1% (4 mg), 6.9% (9 mg), 11.3% (12 mg) vs 4.9% placebo. GI side effects drive discontinuation -- expected with incretin class. Not yet commercially available. Eli Lilly targeted NDA submission for Q4 2026, with projected approval in late 2027 to early 2028 on standard 10-12 month review. Pricing not yet announced. Patients interested should discuss remaining TRIUMPH trial enrollment with their physician.
- –

Orforglipron, FDA-approved April 1, 2026 under the brand name Foundayo, is the first non-peptide (small molecule) oral GLP-1 receptor agonist approved in the United States -- and the first oral GLP-1 for weight loss that can be taken any time of day, with or without food, water, or timing restrictions. Unlike oral semaglutide (which requires SNAC absorption enhancers and strict 30-minute fasting), orforglipron is a small molecule that bypasses GI peptide degradation entirely -- a major real-world adherence advantage for patients who cannot reliably fast in the morning or travel frequently. In the ATTAIN-1 Phase 3 trial (N=3,127, 72 weeks, 10 countries), orforglipron at its highest dose (36 mg) achieved 12.4% average body weight loss in the adherent population (11.1% full population) versus 0.9% placebo. Average absolute weight loss approximately 27.3 pounds. A head-to-head diabetes trial showed orforglipron delivered superior blood sugar control and weight loss vs oral semaglutide (Rybelsus). Side effects: nausea, constipation, diarrhea, vomiting, indigestion, headache, fatigue -- consistent GLP-1 class effects. Cost: Medicare Part D $50/month from July 1, 2026. Commercial savings card: as low as $25/month. Self-pay: $149/month (lowest dose) via LillyDirect. Available from April 6, 2026 at retail pharmacies and telehealth platforms.
- –
Oral semaglutide for weight management received FDA approval on December 22, 2025, with US commercial launch in January 2026 -- the first oral GLP-1 receptor agonist approved for chronic weight management, preceding orforglipron by approximately three months. The mechanism is identical to injectable Wegovy: semaglutide activates GLP-1 receptors in the hypothalamus and gut, suppressing appetite, slowing gastric emptying, and stimulating glucose-dependent insulin secretion. The oral format uses SNAC as an absorption enhancer, requiring strict administration: empty stomach, no more than four ounces of water, no food for 30 minutes after ingestion. The OASIS 4 Phase 3 trial (N=307, 64 weeks) demonstrated 16.6% body weight loss in the adherent population. 34.4% of adherent participants lost 20% or more body weight versus 2.9% placebo. The trial was smaller (N=307) than STEP or SURMOUNT programs; broader cardiovascular outcomes trials (SELECT-O) are ongoing. Side effects mirror injectable semaglutide: nausea, diarrhea, vomiting, constipation, headache, fatigue. Black box warning for thyroid C-cell tumors. Cost: Novo Nordisk self-pay $149/month. Commercial savings card: as low as $25/month. Medicare Part D: $50/month from July 2026. Eligibility: adults with BMI 30+ or BMI 27+ with weight-related comorbidity.
- –

Semaglutide injection remains one of the most clinically important weight loss medications in history. Wegovy (semaglutide 2.4 mg) was FDA-approved for chronic weight management on June 4, 2021 -- the first dedicated GLP-1 medication approved for weight loss in adults, later extended to adolescents aged 12+. Ozempic (semaglutide 1-2 mg) is the same molecule for type 2 diabetes, frequently prescribed off-label for weight management. In STEP 1 (N=1,961, 68 weeks), patients on Wegovy 2.4 mg lost an average of 14.9% of body weight versus 2.4% placebo. Nearly 70% achieved 10%+ weight loss; 50.5% lost 15%+. Most significantly, the SELECT cardiovascular outcomes trial (N=17,604, 104 weeks) demonstrated a 20% reduction in major adverse cardiovascular events in non-diabetic overweight/obese patients with established CVD -- the first proof that a weight loss drug reduces heart attack and stroke risk. This led to FDA label expansion in March 2024. In SURMOUNT-5, head-to-head vs tirzepatide, Wegovy delivered 13.7% vs tirzepatide 20.2%. Side effects: nausea (44%), diarrhea (30%), vomiting (24%), constipation (24%). FDA added gastroparesis warning 2023. Cost: List price ~$1,350/month. Self-pay $149/month (March 2026). Savings card: $25/month. Medicare: $50/month from July 2026.
- –
CagriSema is a fixed-dose combination of semaglutide 2.4 mg (GLP-1 agonist) with cagrilintide 2.4 mg (long-acting amylin analog), administered as a once-weekly subcutaneous co-injection. Amylin is co-secreted with insulin and reduces post-meal glucagon, slows gastric emptying, and contributes to satiety through separate neural pathways -- targeting hunger from two distinct hormonal axes for a combined effect greater than either agent alone. Novo Nordisk filed the NDA with the FDA in December 2025. FDA review ongoing as of mid-2026; decision expected late 2026 to mid-2027. The REDEFINE 1 Phase 3 trial (N=3,400, 68 weeks) demonstrated 22.7% mean total body weight loss. Adherent population: 97.6% achieved 5%+ weight loss; 60.2% achieved 20%+; 40.4% achieved 25%+; 23.1% achieved 30%+. However, REDEFINE 4 (February 2026, 84 weeks) showed CagriSema achieved 23.0% weight loss but failed non-inferiority vs tirzepatide's 25.5% -- a commercial setback. The REIMAGINE trial in T2DM (ADA 2026) showed CagriSema reduced HbA1c and weight more than semaglutide alone. Not yet commercially available. Pricing not announced. Eligibility will mirror existing GLP-1 criteria once approved: BMI 30+ or BMI 27+ with weight-related comorbidity.
- –
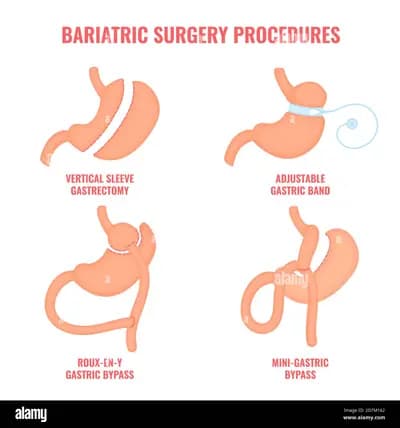
Bariatric surgery remains the most effective long-term weight loss intervention for severe obesity, with decades of data demonstrating durable outcomes that pharmaceutical treatments are still working toward matching. Sleeve gastrectomy permanently removes approximately 80% of the stomach, creating a narrow tube. It reduces capacity, decreases ghrelin (hunger hormone), and alters gut hormone signaling. Gastric bypass creates a small stomach pouch (~30 mL) connected directly to the jejunum, bypassing the duodenum -- combining restriction with malabsorption and profound hormonal changes, including a GLP-1 surge after meals, bile acid remodeling, and favorable gut microbiome shifts. Long-term outcomes: gastric bypass shows 28.3-29% mean total body weight loss sustained at 5-7 years. T2DM remission at 2 years: 63.8% (bypass) vs 53.3% (sleeve). Sleeve: 20-30% total body weight loss with some regain by year 5-10. Risks: 30-day mortality 0.1-0.3%, anastomotic leak 1-2% (bypass), GERD worsening (sleeve), lifelong vitamin supplementation required after bypass. Eligibility per 2022 ASMBS guidelines: BMI 35+ or BMI 30+ with significant metabolic disease. Insurance covers in 48 states. Cost: Sleeve $10,000-$15,000; Bypass $12,000-$30,000 self-pay.
- –
Qsymia is a once-daily extended-release combination of phentermine and topiramate, FDA-approved July 17, 2012, and the most effective non-GLP-1 prescription weight loss option. Extended to adolescents aged 12+. Generic versions are available, making it substantially more affordable than GLP-1 therapies. Phentermine stimulates hypothalamic norepinephrine release, suppressing appetite and increasing energy expenditure. Topiramate has multiple mechanisms including GABA modulation, carbonic anhydrase inhibition, and glutamate receptor effects, collectively reducing caloric intake. At low doses used in Qsymia, each drug stays below its therapeutic threshold for its primary indication -- reducing individual side effects while producing synergistic weight loss. In the EQUIP trial (N=1,267, 56 weeks, BMI 35+), patients on highest dose (15/92 mg) lost 10.9% body weight vs 1.6% placebo; 66% achieved 5%+ loss; 47% lost 10%+. CONQUER trial (N=2,487) showed 9.8% weight loss at 15/92 mg. Critical safety: Teratogenicity (oral cleft defects in infants) -- REMS program required, monthly pregnancy tests mandatory for women of childbearing potential. Black box warning. Also: cognitive impairment known as the Dopamax effect, increased heart rate, metabolic acidosis, kidney stones. Cost: Brand $200-$250/month; generics cheaper. Contraindicated with hyperthyroidism, glaucoma, MAOIs.
- –
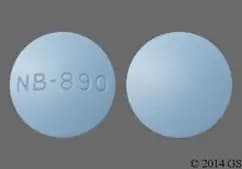
Contrave is an extended-release combination of naltrexone and bupropion, FDA-approved September 10, 2014, targeting central nervous system pathways rather than hormonal mechanisms -- uniquely suited for patients with food reward-driven eating behaviors. Bupropion (dopamine/norepinephrine reuptake inhibitor) activates POMC neurons in the hypothalamus, stimulating melanocyte-stimulating hormone to suppress appetite. Naltrexone (opioid receptor antagonist) blocks opioid autoinhibition on POMC neurons -- amplifying bupropion's activation. Naltrexone also blocks mesolimbic dopamine reward signals from eating calorie-dense foods. This dual-pathway approach addresses both homeostatic (hunger) and hedonic (food reward) components simultaneously -- mechanistically distinct from GLP-1 therapies. In COR-II (N=1,496, 56 weeks), patients lost 6.4% body weight vs 1.2% placebo; 50.5% achieved 5%+ weight loss (vs 17.1% placebo). COR-BMOD added intensive behavioral modification reached 9.3% weight loss. COR-DM showed 5% weight loss in T2DM patients. Side effects: nausea (30%), constipation (19%), headache (18%), increased blood pressure and heart rate. Bupropion carries FDA black box warning for suicidal thoughts/behaviors. Contraindicated with: opioid use (naltrexone blocks opioids), seizure disorder, uncontrolled hypertension, MAOI use, eating disorders. Cost: ~$99/month with manufacturer savings card; widely covered by commercial insurance.
- –
Medical weight loss programs via telehealth platforms -- Hims and Hers, WeightWatchers Clinic (WW Med+), Found Health, Noom Med, and Ro -- represent a structural innovation in how obesity treatment reaches patients rather than a distinct pharmacological intervention. They combine clinician-prescribed medications (primarily GLP-1s), regular virtual medical oversight, and behavioral coaching in subscription models. In 2026, these programs restructured after FDA enforcement against compounded semaglutide accelerated. Most platforms transitioned to brand-name medications with manufacturer self-pay programs, improving safety while increasing medication costs. Hims and Hers Weight Loss: membership $39/month first month, $149/month ongoing, with bundled virtual clinician consultations and GLP-1 access (~$199/month above membership for brand-name injectables). WeightWatchers Clinic (WW Med+): introductory $199/month (through March 2026), standard $349/month integrating WW behavioral program with GLP-1 access. Found Health: compounded semaglutide at ~$189/month with transition to brand-name underway. Clinical research has generally found telehealth-delivered GLP-1 treatment produces weight-loss outcomes comparable to in-person care, when paired with adequate medical oversight. Best suited for patients with BMI 27+ with comorbidity or BMI 30+ who lack access to obesity medicine specialists, prefer virtual care, or benefit from bundled behavioral support alongside pharmacotherapy.
Frequently Asked Questions About GLP-1 Alternatives
Are GLP-1 alternatives as effective as Ozempic? Yes—some newer options match or exceed it. CagriSema and retatrutide both showed greater weight loss than semaglutide alone in Phase 3 trials. Source: [NEJM CagriSema Phase 3 (2024)](https://www.nejm.org/doi/full/10.1056/NEJMoa2405958).
What is the most affordable alternative to GLP-1 injections? Generic versions of Qsymia and Contrave typically cost $30–$100/month with insurance—a fraction of branded GLP-1 injectable prices.
Is the oral semaglutide pill as effective as the injection? Oral semaglutide 50 mg achieved approximately 15% body weight loss in the OASIS 1 trial, comparable to injectable Wegovy 2.4 mg. Source: [OASIS 1 Trial, Lancet (2023)](https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(23)01185-6/fulltext).
Image credits
- Orforglipron (Foundayo): Bing Images / www.straighthealthcare.com
- Semaglutide Injection (Wegovy / Ozempic): Semaglutide / Wikipedia
- CagriSema (Cagrilintide + Semaglutide): Bing Images / medcare-healthclinic.com
- Bariatric Surgery (Sleeve Gastrectomy / Gastric Bypass): Bing Images / c8.alamy.com
- Qsymia (Phentermine / Topiramate ER): Bing Images / static.wixstatic.com
- Contrave (Naltrexone / Bupropion ER): Bing Images / www.grxstatic.com
Related Videos
Frequently asked questions
What are GLP-1 alternatives for weight loss?
GLP-1 alternatives include dual GIP/GLP-1 agonists like tirzepatide (Mounjaro/Zepbound), oral weight loss medications like orlistat, and next-generation treatments such as amycretin and retatrutide currently in clinical trials. These options target different metabolic pathways to reduce appetite, improve insulin sensitivity, or block fat absorption.
Are GLP-1 alternative weight loss treatments as effective as semaglutide (Ozempic/Wegovy)?
Some next-generation treatments have demonstrated superior weight loss results in clinical trials — for example, tirzepatide (Zepbound) has shown average body weight reductions of up to 22.5%, compared to approximately 15% with semaglutide. Newer triple-agonist drugs like retatrutide are showing even greater potential in early-phase studies.
What are the side effects of GLP-1 alternatives?
Common side effects of GLP-1 class alternatives include nausea, vomiting, diarrhea, and constipation, particularly during dose escalation. The specific side effect profile varies by drug class — for example, oral fat blockers like orlistat primarily cause gastrointestinal effects, while newer peptide-based treatments share similar tolerability profiles to GLP-1 medications.
Are there non-injectable GLP-1 alternatives available in 2026?
Yes, oral options are increasingly available in 2026, including oral semaglutide (Rybelsus) for type 2 diabetes, and newer oral GLP-1 formulations in advanced development for weight loss. Non-GLP-1 oral alternatives such as orlistat and bupropion/naltrexone (Contrave) also remain FDA-approved options.
Who should consider GLP-1 alternatives for weight loss?
GLP-1 alternatives may be appropriate for individuals with obesity (BMI ≥ 30) or overweight (BMI ≥ 27) with at least one weight-related health condition who cannot tolerate GLP-1 medications, face access or cost barriers, or have not achieved sufficient results with first-line treatments. A healthcare provider should guide treatment selection based on individual medical history and goals.
Rank it your way
Remix this list into your own ranking, or head to the play hub for every game mode and community breakdown — blind mode, challenges, tier lists, and more.
You Might Also Like

Top 10 Sleep Products That Insomniacs Swear Actually Work
best sleep products insomniacs actually swear by

Top 10 Postpartum Recovery Products Nobody Tells You About
best postpartum recovery products

Top 10 Home Gym Equipment Worth the Investment
best home gym equipment investments

Top 10 GLP-1 Friendly Foods for Easier Digestion in 2026
#1 Plain Greek Yogurt (Nonfat) · #2 Eggs · #3 Skinless Chicken & Turkey Breast

Top 10 Healthiest Foods Ranked – Science-Proven Best Picks for 2026
#1 Wild Salmon · #2 Blueberries · #3 Leafy Greens (Spinach, Kale)
Top 10 Ways AI Is Revolutionizing Healthcare in 2026
#1 AI-Powered Medical Imaging Diagnosis · #2 Drug Discovery Acceleration · #3 Predictive Patient Risk Scoring